Can the Kaiser Score with Breast MRI Improve Clarity for BI-RADS 0 and 4 Assessments on Mammography and Ultrasound?
Breast Imaging Reporting and Data System
BI-RADS is the standardized vocabulary and reporting framework breast radiologists use to describe findings and assign a final assessment with a recommended next step. Maintained by the American College of Radiology, it spans the breast across mammography (including tomosynthesis), ultrasound, MRI, and contrast-enhanced mammography, so a report means the same thing to anyone who reads it. Its hallmark is a numbered assessment scale that ties each imaging conclusion to a management recommendation. It is the dominant breast-imaging lexicon worldwide and, in the United States, is woven into federal mammography reporting requirements.
The first major overhaul in over a decade and the largest expansion yet (the illustrated guide was rebranded from 'Atlas' to 'Manual'). Breast-density reporting became a mandatory standalone section across all modalities, tomosynthesis was formally folded into how masses are characterized, and contrast-enhanced mammography was elevated to a full core modality. The lexicons were modernized — ultrasound gained a 'non-mass' concept, several ambiguous MRI terms were retired and new descriptors added (with recognition of abbreviated MRI protocols), and categories 0 and 6 were clarified rather than renumbered. It matters because reporting now better matches how breast imaging is practiced today.
The reference standard until v2025. It delivered a comprehensive update across mammography, ultrasound, and MRI, sharpened breast-density language toward a composition/masking emphasis, and strengthened management and outcome-monitoring guidance.
A major expansion that added dedicated lexicons for breast ultrasound and breast MRI for the first time, moving BI-RADS beyond mammography, and introduced the 4A/4B/4C subdivision to better stratify biopsy risk.
Broadened the illustrated atlas with feature illustrations and added practice-auditing guidance and sample reports to support quality assurance.
A refinement update that improved descriptor clarity and consistency over the original.
The original, mammography-only release that established standardized terminology, a structured report format, and the numbered assessment-category concept to cut interpretive variability.
At its core, BI-RADS sorts every study into a small set of numbered final assessment categories, conventionally 0 through 6, where each number bundles a level of suspicion with the action it implies — from 'more imaging needed' through 'benign' and 'probably benign' to escalating degrees of cancer concern and, finally, already-proven cancer. The scale is ordered so a higher number broadly signals greater concern or a more definitive next step, and the 'suspicious' tier is further split into low/intermediate/high sub-levels. Separately, the system standardizes how findings are described (shape, margin, density, calcifications, enhancement, breast density). Consult the official ACR BI-RADS v2025 Manual for the exact criteria, definitions, and management language.
These are our plain-language summaries. For the exact criteria, thresholds, and management rules, see the official source.
Can the Kaiser Score with Breast MRI Improve Clarity for BI-RADS 0 and 4 Assessments on Mammography and Ultrasound?
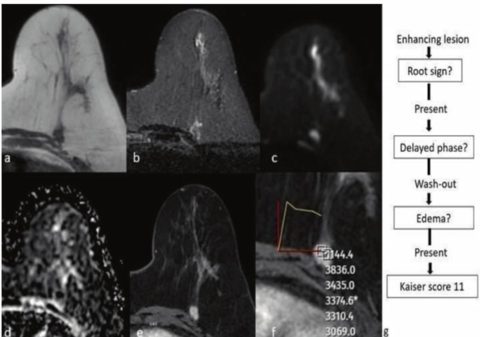
In a small study of 99 women with BI-RADS 0 or 4 mammography/ultrasound, breast MRI Kaiser score (>5) had 97% sensitivity and 98.3% NPV for malignancy, vs 60.6% and 83.5% with MRI BI-RADS category 4. One cancer scored 5, so score cannot safely exclude malignancy.
Kaiser score outperforms MRI BI-RADS for inconclusive breast findings
Among 271 BI-RADS 4 breast ultrasound lesions, an FDA-cleared AI tool classified 60.6% of benign lesions as BI-RADS 2 or 3, potentially reducing benign biopsies. However, 9.5% of malignant lesions were downgraded, warranting careful integration with radiologist judgment.
Deep-learning virtual dynamic contrast-enhanced (DCE) breast MRI reached 92% sensitivity vs 96% for standard gadolinium-enhanced DCE, with accuracy 76% vs 77% and no significant differences in BI-RADS or background enhancement in a 592-exam study.
In women with newly diagnosed breast cancer, additional ipsilateral BI-RADS 3 lesions on ultrasound had a malignancy rate of 7.5% (41/544), vs 0.9% (13/1451) for contralateral lesions. Same-quadrant location, architectural distortion, and calcifications predicted malignancy.
ACR says BI-RADS criteria may lead to unnecessary pediatric procedures
ACR: BI-RADS for adults, not children
ACR Urges Caution When Using BI-RADS for Pediatric Breast Masses
American College of Radiology Urges Caution When Using BI-RADS for Pediatric Breast Masses | Newswise
VIDEO INTERVIEW | Dr. Božinovska: What does BI-RADS mean and when is mammography necessary?
Correction: Grade III Ductal Carcinoma In Situ Arising Within a Long-Standing Fibroadenoma: A Case Report Illustrating the Limits of Shape-Based Breast Imaging Reporting and Data System (BI-RADS) and AI-Assisted Ultrasound Assessment.
In 181 breast microcalcification lesions, a digital breast tomosynthesis radiomics plus clinical nomogram had validation AUC 0.790, below the clinical-only 0.881, suggesting combined modeling needs optimization.
Multimodal AI model combining ultrasound radiomics, hemodynamics, and clinical data achieved AUC 0.95 (95% CI 0.91-0.99) and 100% sensitivity for classifying BI-RADS 4a breast nodules, potentially avoiding 32.4% of unnecessary biopsies.
September’s most-viewed Diagnostic Imaging video interviews cover newly FDA-approved PET imaging agents for cardiac amyloidosis and glioma, BI-RADS updates, and CT/MRI research linking bone loss to cognitive decline and diabetes.
A benign-appearing breast mass was classified as BI-RADS 2 by an AI ultrasound tool based on shape. However, shear-wave elastography showed markedly elevated stiffness (max 135.48 kPa), leading to biopsy that revealed high-grade DCIS arising in a fibroadenoma. Malignancy can ret…
How the COVID-19 Pandemic Led to Updated BI-RADS Guidance on Addressing Axillary Lymphadenopathy
Ultrasound Nonmass Lesion in BI-RADS v2025: A Primer.
Deep learning BI-RADS model for breast MRI yielded an AUC of 0.767 (95% CI 0.693–0.830) vs radiologist AUC 0.913 (0.857–0.952) on external validation of 158 exams, a significant difference of 0.146 (P=0.0001). At a BI-RADS >3 threshold, it flagged 54.7% of benign exams as low-ri…
In 279 excised breast lesions in patients under 20, none were malignant and 87% were fibroadenomas, yet 55% were Breast Imaging Reporting and Data System (BI-RADS) 4—adult estimates overpredict pediatric cancer risk.
Ikonopedia updates breast reporting platform for BI-RADS v2025
Ikonopedia Announces New Release Supporting BI-RADS® v2025 (6th Edition)
A 'Wake-Up Call' for BI-RADS 3 Audits
Video: Stamatia Destounis, MD, FACR, Discusses Key Changes for the Updated BI-RADS System
<![CDATA[Video: Stamatia Destounis, MD, FACR, Discusses Key Changes for the Updated BI-RADS System]]>
BI-RADS v2025 formally incorporates nonmass lesions (NMLs) on breast ultrasound, which have a high malignancy rate. A pictorial review classifies NMLs by distribution—segmental, linear, focal, regional—showing benign/malignant cases, descriptors, and multimodality correlation.
In 539 triple-negative breast cancers, HER2-low vs HER2-0 tumors showed different ultrasound vascularity (avascular: 6.3% vs 12.0%) and radiomics features; overall survival was similar, but HER2-low was associated with improved event-free survival in non-pCR patients.
Reasoning large language models (LLMs) scored higher than conventional ones for BI-RADS educational questions (median 3.7 vs 2.7, P<0.001). Performance fell for multifaceted clinical scenarios (reasoning models Δmedian -1.3). ChatGPT-o1 and Deepseek-R1 led. Language affected som…
Bringing BI-RADS Into the Current Era of Breast Imaging.
BI-RADS is effectively the universal lexicon for breast imaging, with little real competition — it is the template that later 'RADS' systems (PI-RADS, LI-RADS, and others) were modeled on. In the United States its use is reinforced by federal mammography regulation, which cements its dominance over ad hoc reporting. Where alternatives exist they tend to be complementary rather than rival: automated/volumetric breast-density software, for example, maps its output back onto BI-RADS density classes rather than replacing the framework.
BI-RADS underpins large national audit datasets, and its predictive value rises steeply across the suspicious sub-tiers — reported positive predictive values climb from roughly a third for 4A to the high-80s–90s percent for 4B/4C and category 5 — which validates the stratification while exposing that sub-categorizing category 4 is subjective and reader-dependent. Inter-reader reproducibility is generally substantial but imperfect, with breast-density assignment in particular showing meaningful variability between editions and experience levels. Historical analyses credit BI-RADS with materially reducing reporting ambiguity and enabling outcomes monitoring since the 1990s. Recurring criticisms — interpretive variability in the probably-benign and suspicious zones, and density-assessment subjectivity — are explicitly among the issues the 2025 6th edition set out to address.
RadPigeon is an independent radiology news digest and is not affiliated with or endorsed by American College of Radiology (ACR). “BI-RADS” is a trademark of its owner and is named here only to refer to the system. Always consult the official source for the exact, current criteria.